马上注册,阅读更多内容,享用更多功能!
您需要 登录 才可以下载或查看,没有账号?立即注册 
×
R+ Resection for Clinical Stage III Non-Small Cell Lung Cancer: Should We Have Just Given Chemoradiation?
临床III期非小细胞肺癌R+切除术:化放疗还是手术?
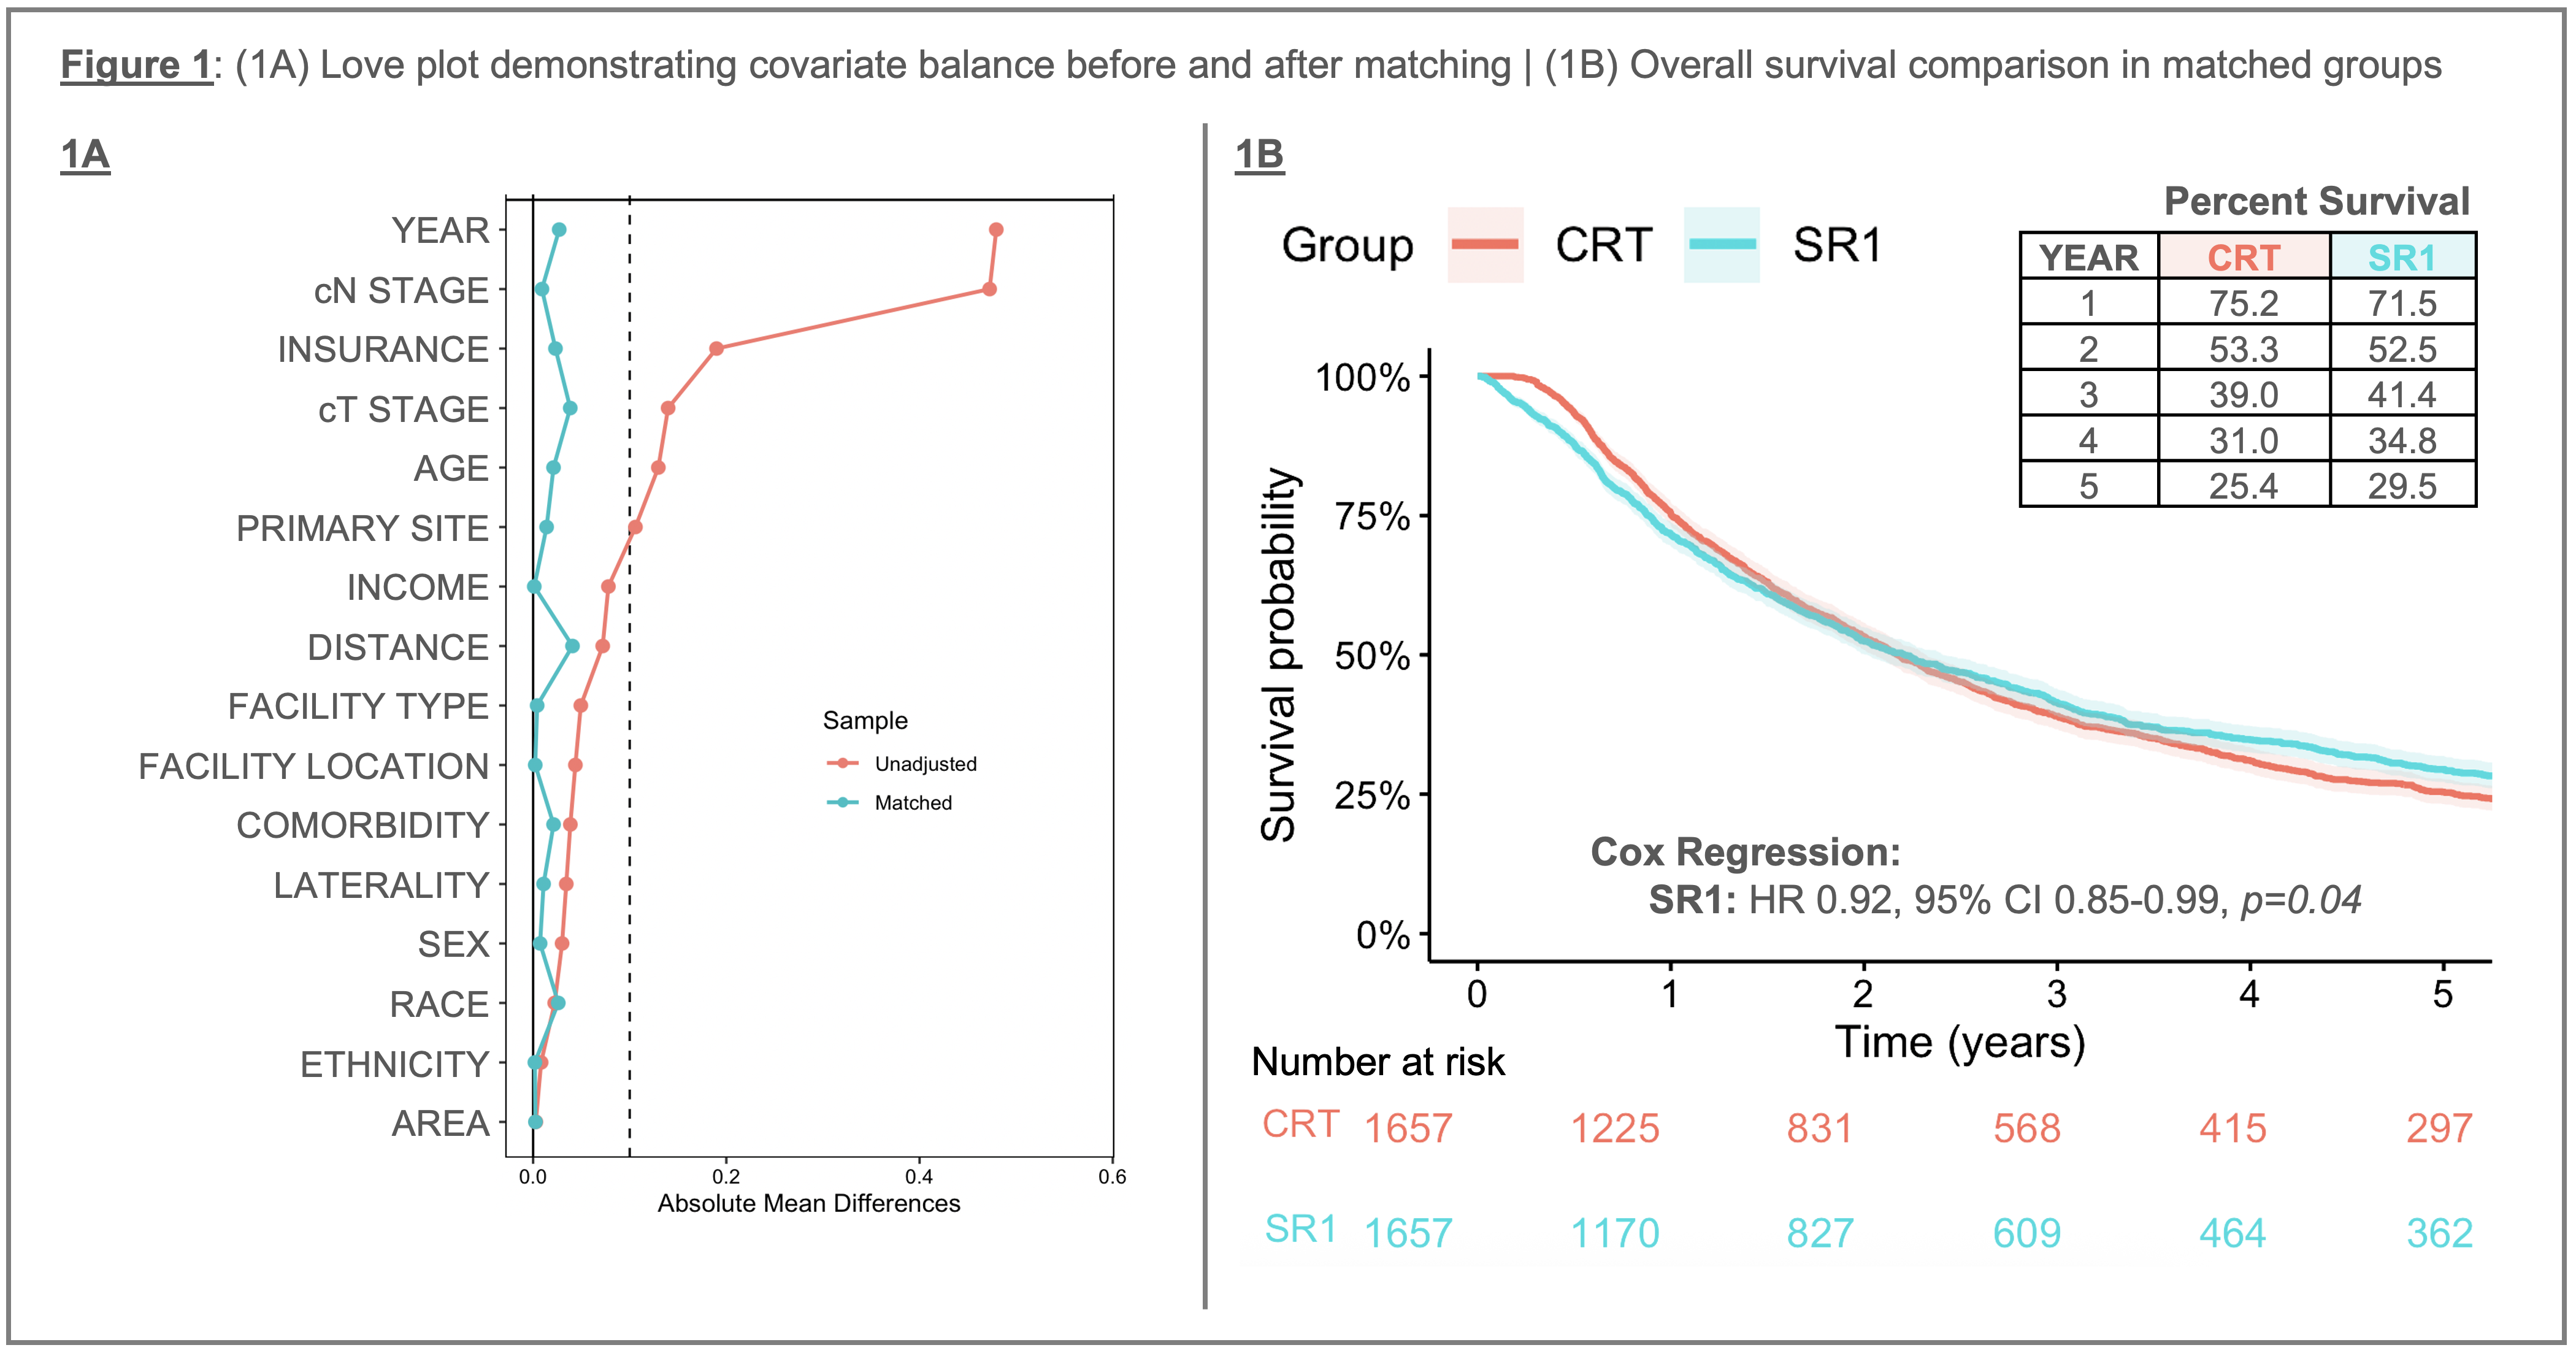
SR1患者在术后一年生存差于化放疗 (71.5% vs. 75.2%) , 但在2.5年后则优于仅行 化放疗而未手术者 (46.9% vs. 45.2%) (HR 0.92, 95% CI 0.85-0.99, p=0.04; Figure 1)。
提示不可切除手术的人群转化治疗可能的价值。
Objective:
The optimal treatment standard for patients with clinical stage III (cIII) non-small cell lung cancer (NSCLC) is debated, with resectability playing a critical role. While surgeons must try to avoid R+ resections, chemoradiation is also known to frequently leave patients with residual local disease. The objective of this study is to compare outcomes in patients with cIII NSCLC treated with chemoradiation (CRT) versus surgery with positive margins.
Methods:
From the National Cancer Database, we identified patients with cIII NSCLC (excluding N3) treated with either CRT or surgery with an R1 outcome (SR1) (2004-2022). Logistic regression evaluated predictors of treatment modality. Survival in matched groups was analyzed by Kaplan-Meier and Cox regression.
Results:
Of 72,908 patients, 96.5% (n=70,324) received CRT and 3.5% (n=2,584) underwent SR1. The SR1 group accounted for 6.2% of those patients who underwent surgery for cIII disease (n=41,873) and was associated with left-sided (aOR 1.13, 95% CI 1.02-1.25), middle lobe (aOR 1.60, 95% CI 1.29-1.98), and lower lobe (aOR 1.33, 95% CI 1.19-1.48) disease. CRT use was associated with increasing age (aOR 1.01, 95% CI 1.01-1.02), cT4 disease (aOR 1.69, 95% CI 1.47-1.95), and node-positivity (aOR 4.24, 95% CI 3.62-4.95). A total of 541 (20.9%) SR1 patients had neoadjuvant therapy, including 166 (n=6.2%) with immunotherapy. The majority of resections were open (57.8%, n=909) and the most common operation was a lobectomy (66.6%, n=1722). Of the SR1 cohort, 9.4% (n=244) had nodal upstaging and 51.9% (n=1339) had identical clinical and pathologic nodal stage. Adjuvant therapy rates in the SR1 group were 51.4% (n=1329) for systemic therapy and 43.3% (n=1118) for radiation. In a matched cohort comparing CRT and SR1 groups, SR1 was initially associated with worse survival (71.5% vs. 75.2%) at one year but improved survival after 2.5 years (46.9% vs. 45.2%) (HR 0.92, 95% CI 0.85-0.99, p=0.04; Figure 1).
Conclusions:
Survival after incomplete resection appears comparable to that seen in patients undergoing nonsurgical therapy, suggesting that surgery could be reasonably considered over CRT even in marginally resectable patients. With higher pathologic response rates identified in the era of neoadjuvant chemoimmunotherapy, it is anticipated that patients with cIII NSCLC will increasingly be offered surgical management.
Grace Ha (1), Olga Ostrovetsky (1), Tamar Nobel (1), Marc Vimolratana (1), Brendon Stiles (1), Neel Chudgar (1), (1) Montefiore Medical Center, Bronx, NY
|

